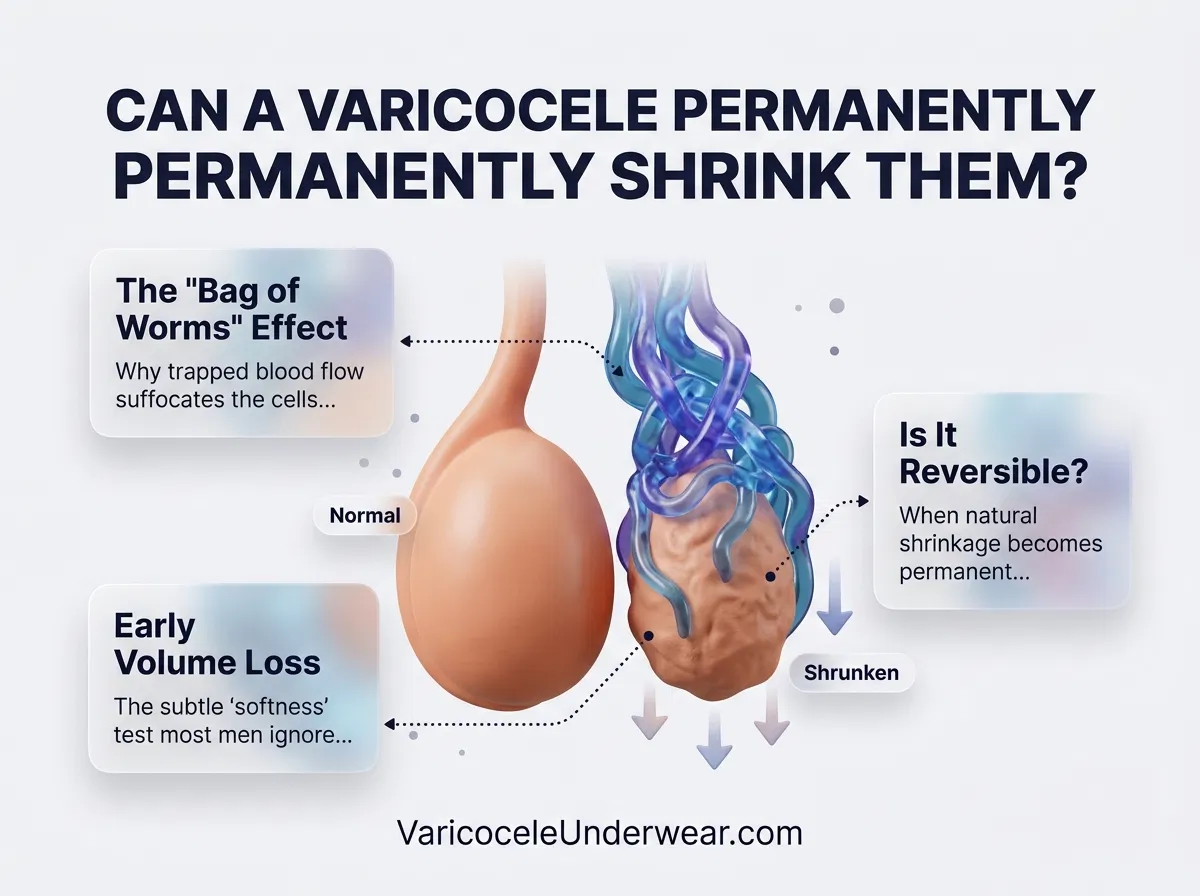
When incompetent valves in the pampiniform plexus allow venous blood to pool around the testicle, the resulting chronic venous hypertension restricts arterial inflow and elevates local temperature. Understanding why varicocele causes testicular shrinkage requires looking directly at the microscopic changes inside the seminiferous tubules. The continuous pooling of deoxygenated blood creates an ischemic environment where tissue lacks adequate oxygen. Over time, persistent hypoxia and germ cell apoptosis trigger the systematic destruction of developing sperm cells. Because germ cells make up roughly seventy to eighty percent of total testicular mass, their progressive death results in measurable tissue reduction. Catching the early signs of volume loss gives men the best opportunity to protect their hormone levels, preserve fertility, and halt ongoing gonadal injury before structural damage becomes permanent.
The Pathophysiology of Testicular Shrinkage
To grasp how volume decreases, one must first look at normal scrotal anatomy. The testicles rely on an intricate vascular network called the pampiniform plexus. This collection of tiny veins wraps around the testicular artery, operating as a countercurrent heat exchanger. Arterial blood flowing from the abdominal cavity arrives at core body temperature, roughly 37 degrees Celsius. Before that warm blood reaches the delicate seminiferous tubules, the cooler venous blood ascending through the pampiniform plexus absorbs the thermal energy. This mechanism cools the testis down to between 33 and 34 degrees Celsius, an absolute requirement for healthy spermatogenesis.
When internal vein valves malfunction, retrograde blood flow occurs under gravitational pressure. Venous blood backs up into the internal spermatic vein, generating abnormally high hydrostatic pressure throughout the scrotum. This vascular engorgement neutralizes the countercurrent cooling system. Instead of heat dissipating away from the gonad, the testis remains bathed in warm, stagnant blood. In clinical practice, men experiencing varicocele testicular shrinkage exhibit sustained hyperthermia inside the scrotal sac. Even an elevation of one to two degrees disrupts protein synthesis within the germinal epithelium. Sustained exposure to body heat causes Sertoli cells, which physically nurse and feed maturing sperm cells, to degrade their internal architecture, triggering early tissue atrophy.
The secondary consequence of elevated venous pressure involves microcirculatory congestion. Under healthy physiological conditions, high pressure inside the capillaries pushes nutrient-rich fluid into the interstitium, while low venous pressure draws fluid and metabolic waste back out. A varicocele reverses this pressure dynamic. Elevated backpressure inside the pampiniform veins creates capillary hypertension, which prevents clean arterial blood from entering the capillary beds. The tissue starves of glucose and oxygen. If left unmanaged, the untreated varicocele long term effects extend well beyond cosmetic asymmetry, causing irreversible interstitial fibrosis, basement membrane thickening, and ongoing gonadal volume contraction.
Chronic Hypoxia and Germ Cell Apoptosis
Apoptosis refers to programmed cell death, a normal biological process used to remove damaged or defective cells. In a healthy testicle, baseline apoptosis quietly clears genetically abnormal spermatocytes. Under conditions of chronic ischemia, however, this orderly cleanup accelerates into mass destruction. Testicular tissues consume high rates of oxygen because dividing germ cells undergo rapid cellular mitosis and meiosis. When poor venous drainage traps deoxygenated blood in the scrotum, the partial pressure of oxygen inside testicular tissue plummets. This creates an environment of sustained hypoxia.

Discover specialized varicocele underwear designed for daily comfort, support, and recovery — a more targeted option for men who want support without compromise.
Discover the Recommended OptionHypoxic stress damages the mitochondria within primary spermatocytes and spermatogonia. As oxygen deprivation deepens, mitochondrial membranes become permeable, leaking cytochrome c into the cytoplasm. This leakage activates proteolytic enzymes known as caspases, which cleave essential cellular structural proteins and fragment nuclear DNA. Published testicular tissue histology research demonstrates that men with grade 2 and grade 3 varicoceles show significantly higher apoptotic indexes inside their seminiferous tubules than healthy controls. While mature Sertoli and Leydig cells show higher tolerance to oxygen deprivation, immature germ cells die rapidly. As layer upon layer of germ cells self-destruct without replacement, the tubular walls collapse inward, directly causing the gonadal volume to shrink.
Venous congestion starves delicate testicular tissues of fresh arterial oxygen by trapping spent blood within the pampiniform vascular bed. When microvascular blood flow slows to a crawl, toxic metabolites accumulate while cellular oxygen levels fall below critical thresholds. Relieving this mechanical pooling is essential for maintaining healthy microcirculation. Utilizing specialized oxygenating varicocele support briefs from VaricoceleUnderwear.com helps lift the scrotal sac, realign congested vessels, and promote steady venous outflow. By lifting hydrostatic pressure off the delicate internal spermatic veins and integrating thermal dissipation fabrics, these garments support testicular health and protect vulnerable parenchymal tissue from ongoing hypoxic stress.
Healthy Anatomy vs. Atrophic Volume Metrics
Clinicians evaluate testicular volume using both comparative physical examination and high-resolution scrotal ultrasonography. The table below outlines standard anatomical parameters compared to measurements observed during progressive stages of varicocele-induced atrophy.
| Clinical Parameter | Healthy Adult Testis | Varicocele-Affected (Early Loss) | Advanced Testicular Atrophy |
|---|---|---|---|
| Mean Ultrasound Volume | 15 to 25 mL | 11 to 14 mL (10% to 19% asymmetry) | Under 10 mL (>20% asymmetry) |
| Inter-Testicular Discrepancy | Under 10% volume difference | 10% to 19% smaller than unaffected side | Equal to or greater than 20% size difference |
| Seminiferous Tubule Diameter | 180 to 250 micrometers | 140 to 175 micrometers | Under 140 micrometers with lumen collapse |
| Johnsen Spermatogenesis Score | Score 9 to 10 (Full spermatogenesis) | Score 6 to 8 (Maturation arrest) | Score 1 to 5 (Extensive sclerosis) |
| Tissue Consistency (Palpation) | Firm, elastic, uniform tension | Softened, spongy, slight loss of turgor | Noticeably flaccid, shrunken, doughy |
| Mean Scrotal Temperature | 33.5°C to 34.5°C | 35.0°C to 36.0°C | 36.2°C to 37.0°C (Near core temperature) |
Recognizing Early Signs of Volume Loss
Detecting volumetric loss before advanced tissue wasting develops is vital for clinical preservation. The American Urological Association (AUA) and the European Association of Urology (EAU) define clinically significant atrophy as a volume discrepancy greater than 20 percent, or a loss exceeding 2 milliliters compared to the contralateral, unaffected testis. In clinical practice, men rarely experience sudden testicular shrinkage overnight. Instead, the process unfolds gradually over months or years, often starting with subtle changes in tissue density.

The earliest physical indicator is often a shift in tissue turgor. A healthy testicle feels firm and resilient, similar to the muscular pad at the base of the thumb. When chronic hypoxia begins degrading the germinal layer, the affected testicle softens, feeling spongy or loose on palpation. Men frequently notice this softness before any measurable loss in outer dimensions occurs. Visual asymmetry often follows. While the left testicle naturally hangs slightly lower than the right in most men due to venous anatomy, a noticeable size gap where the left testis looks markedly smaller or retracted warrants clinical attention. Exploring varicocele testicular atrophy reversibility reveals that catching this disparity early gives germ cells their greatest chance to regenerate once normal blood flow resumes.
Physical sensations often accompany these architectural shifts. Men report an escalating dull ache in the groin or scrotum, particularly after prolonged standing, intense physical training, or at the end of a warm day. This discomfort reflects venous distension and elevated interstitial tissue pressure. A heavy, pulling sensation occurs as gravitational forces drag down the engorged pampiniform veins. Upon careful self-examination, men may also feel the classic “bag of worms” mass of dilated veins above or behind the superior pole of the testis. These physical warning signs frequently create deep anxiety regarding future fertility, testosterone levels, and sexual health.
Clinical Evaluation and Protective Strategies
When physical changes appear, accurate clinical staging is the essential next step. A urologist will perform a physical exam in both supine and standing positions, often asking the patient to perform a Valsalva maneuver (bearing down) to make dilated veins prominent. High-resolution scrotal color Doppler ultrasound serves as the gold standard for diagnostic confirmation. Doppler ultrasound measures venous retrograde flow velocity during Valsalva maneuvers and calculates precise testicular dimensions in three axes (length, width, depth) using the Lambert formula (Length × Width × Depth × 0.71) to evaluate exact volume.
For individuals managing mild discomfort or early vascular dilation, conservative lifestyle strategies provide meaningful relief. Avoiding sustained heat sources such as hot tubs, saunas, and restrictive tight clothing helps maintain a lower scrotal temperature. Selecting the best varicocele underwear provides gentle scrotal elevation, which aids venous return through secondary collateral channels and prevents gravitational blood pooling during daily walking or exercise.
If ultrasound monitoring confirms progressive volume reduction greater than 20 percent, or if semen analysis demonstrates declining sperm concentration and motility, surgical or endovascular intervention may be warranted. Microsurgical subinguinal varicocelectomy allows direct ligation of abnormal veins under high magnification while sparing testicular arteries and lymphatic vessels. Catheter-based percutaneous embolization provides a minimally invasive alternative that blocks retrograde flow using coils or sclerosant agents. Following successful interruption of venous pooling, testicular microcirculation stabilizes. In younger men and adolescents, correcting venous hypertension frequently produces catch-up testicular growth, proving that early intervention can successfully protect functional testicular tissue.
Related Articles



Choose Varicocele Support Designed for Cooling, Lift, and Daily Comfort
You’ve seen why regular underwear often falls short. Now view the purpose-built option made to reduce heaviness, improve support, and feel comfortable enough for everyday wear.